

Surgical · 11 min read
Functional and Cosmetic Rhinoplasty: Breathing and Shape in London
By Dr Hassan Soueid · GMC 6107783 · Medical Director, Kensington Cosmetic Clinic
Published 15 November 2026
TL;DR. Septorhinoplasty combines work inside the nose to improve airflow with changes to its outward shape, and for the right person it can help both, but it cannot fix every cause of a blocked nose, recovery takes months, and understanding why you struggle to breathe matters more than any profile you have in mind.
Many people who come to see us about their nose start with one concern and discover a second. Someone who has disliked a bump on their bridge since their teens mentions, almost in passing, that they have never breathed well through one side. Someone else arrives because their nose has felt blocked since a sports injury, and only later admits they would also like it to look straighter. In London we see both journeys regularly, and the honest answer is that breathing and shape are rarely fully separate. This guide explains how functional and cosmetic rhinoplasty fit together, what surgery can realistically change and where it falls short.
Why breathing and shape belong in the same conversation
The nose is a single structure with two jobs. Its framework of bone and cartilage gives it its shape, and the same framework holds the airway open. The septum, the wall of cartilage and bone that divides the nose into two passages, supports the bridge and tip from inside. The side walls, made of thin cartilage, determine both how the nose looks from the front and how well it resists collapsing when you breathe in hard.
Because of this, surgery on the outside of the nose has consequences for the inside, and the reverse is also true. Older approaches to cosmetic rhinoplasty often focused on removing tissue: taking down a hump, narrowing the tip, reducing overall size. Some patients were left with a nose that looked smaller but breathed worse, because the supporting structures had been weakened. Current thinking puts far more emphasis on preserving and reinforcing support, which is one reason a breathing assessment forms part of every rhinoplasty consultation with us, whether or not airflow is your main concern.
Septorhinoplasty simply describes an operation that addresses the septum and the external shape at the same time. A septoplasty on its own deals with the internal wall and is intended to change function, not appearance. In practice many operations sit somewhere between the two, and the balance depends on what is causing your symptoms and what you would like to change. If you are still deciding whether surgery is right for you at all, our guide to rhinoplasty candidacy and realistic goals covers the broader picture. This article focuses on where breathing and appearance meet.
How the nose moves air: septum, turbinates and valves
It helps to understand a little anatomy, because the cause of a blocked nose determines whether surgery is likely to help.
The septum. Very few septums are perfectly straight, and a mild deviation is normal and often causes no symptoms. A more significant bend, present from birth or caused by injury, can narrow one or both passages. A deviation near the front of the nose tends to matter more than one further back, because the front of the airway is already the narrowest part.
The turbinates. These scroll-shaped structures on the side walls of the nose warm and humidify the air you breathe, and they naturally swell and shrink through the day. In people with allergies or chronic rhinitis the lower turbinates can stay enlarged and contribute heavily to congestion. They are sometimes reduced during surgery, but conservatively, because removing too much can cause a dry, crusting nose that paradoxically feels blocked.
The internal nasal valve. This is the narrowest point of the airway, where the septum meets the upper side wall cartilages. Small changes here make a large difference to airflow. A narrow valve can be natural, can follow an injury, or can result from previous rhinoplasty where the middle of the nose was narrowed or lost support.
The external nasal valve. This is the area just inside the nostrils, supported by the lower cartilages that also shape the tip. If these cartilages are weak, the nostril walls can draw inwards on a deep breath, especially during exercise. Some people notice this themselves in the mirror.
Beyond structure sit the lining conditions: allergic and non-allergic rhinitis, nasal polyps, chronic sinusitis and the rebound congestion that follows overuse of decongestant sprays. These are medical problems, not shape problems, and reshaping cartilage will not treat them. Distinguishing structural blockage from lining-related blockage is the most important step before anyone considers an operation.
Finding the real cause at our Kensington clinic
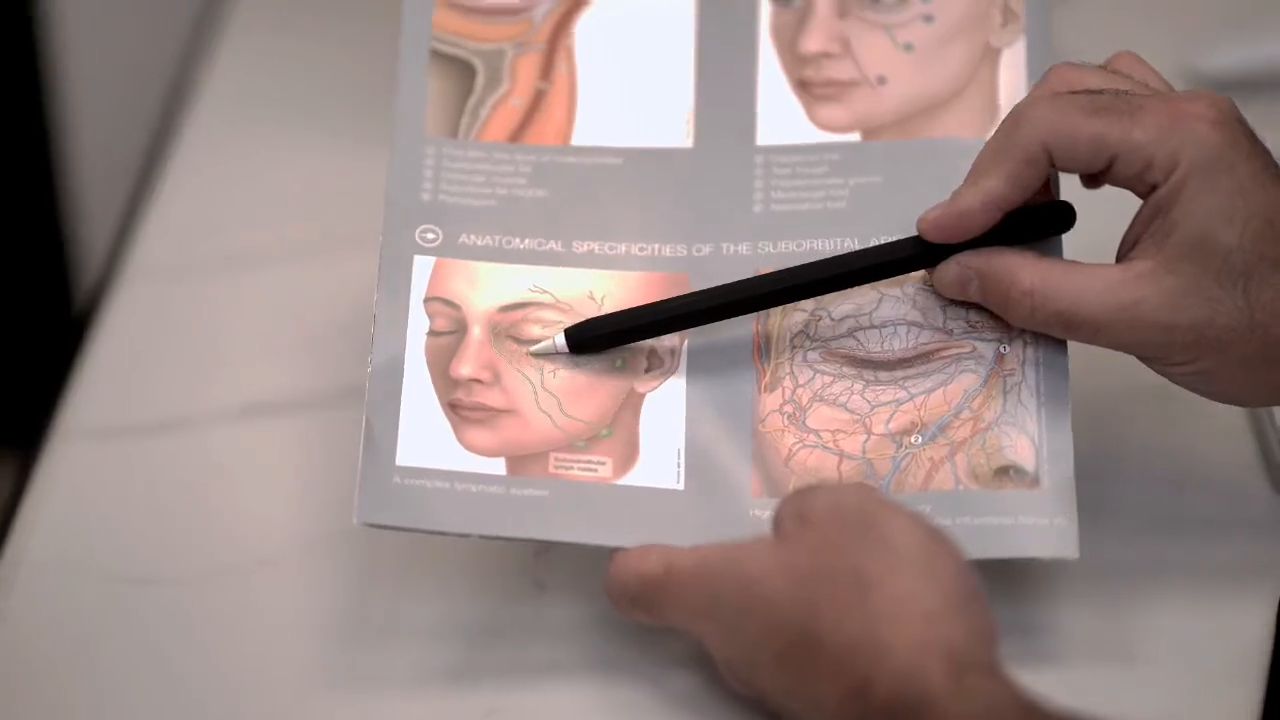
A breathing assessment starts with a conversation, not a mirror. During a doctor-led consultation at our clinic in Kensington, west London, we ask whether the blockage is on one side or both, whether it is constant or comes and goes, whether it changes with the seasons, lying down or exercise, and whether you have had injuries, previous surgery or long-term use of nasal sprays. Symptoms that alternate between sides and worsen with pollen or dust point more towards the lining. Symptoms that are fixed, one-sided and date back to a knock on the nose point more towards structure.
Examination includes looking at the nose from several angles, assessing the strength of the side walls and tip, and looking inside with a light. Gently lifting the cheek skin to open the valve area, sometimes called the Cottle manoeuvre, can suggest whether the valve is contributing, although it is only one piece of information. In some cases imaging, or referral to an ear, nose and throat surgeon or back to your GP, is the right next step, particularly where there are signs of sinus disease, polyps or possible sleep-disordered breathing.
We will also ask what you would like to change about the appearance of your nose, if anything. Some patients want nothing cosmetic at all; others have a clear aesthetic aim and only a mild functional issue. Honesty on both sides matters here, because the plan for someone who wants the outside to look unchanged is quite different from the plan for someone hoping for a visibly different profile.
Medical treatment is often worth trying first. A correctly used steroid nasal spray, allergy management or stopping decongestant overuse helps some people enough that surgery is not needed. If it helps only partly, that tells us something useful too.
What septorhinoplasty can and cannot fix
When the main cause is structural, septorhinoplasty can address several things in one operation. A deviated septum can be straightened or partly removed and repositioned, while leaving enough of it in place to support the nose. Collapsed or narrow valves can be opened and strengthened, often using small grafts of the patient's own cartilage, typically taken from the septum itself. A twisted nose can be straightened externally at the same time as the airway is improved internally. Enlarged turbinates can be reduced where that is appropriate. Alongside this, cosmetic changes such as reducing a hump, refining the tip or adjusting the length of the nose can be made, provided they do not undermine the airway.
The limits are just as important. Septorhinoplasty does not treat allergies, rhinitis or chronic sinus infection, so if these are major contributors you may still feel congested afterwards. It is not a reliable treatment for snoring, and it is not a cure for obstructive sleep apnoea, even though improving nasal airflow can sometimes make other treatments easier to tolerate. It cannot restore a sense of smell that has been lost for other reasons. It also cannot promise that every part of the nose will look perfectly symmetrical, because faces are not symmetrical and healing varies between individuals.
Some people have a nose that looks open on examination yet feel blocked, and others have a significant deviation yet notice little. How much someone's breathing changes after surgery is not something any doctor can predict precisely. We can explain whether the structural findings fit your symptoms and how likely surgery is to help in that context, but we will not tell you that you will breathe perfectly afterwards.
Non-surgical options deserve a mention. Some people ask whether a so-called non-surgical nose job using dermal fillers could solve the problem. Filler can sometimes disguise a small bump or a slight dip in the profile, but it does nothing for the airway. The nose also carries particular vascular risks with filler, so it needs careful discussion rather than being treated as a quick fix.

Changing the shape without compromising airflow
When you want both a better-functioning nose and a different appearance, planning becomes a balancing act, and every aesthetic change has to be judged by its effect on support.
Reducing a hump on the bridge is a common request. When it is removed, the roof of the nose is opened and the upper side cartilages can lose their connection to the septum. If this area is not reconstructed, the middle third of the nose can narrow and fall inwards over time, changing the look and pinching the internal valve. Surgeons often rebuild it using spreader grafts or by folding the patient's own cartilage to hold the valve open, adding structure rather than simply taking it away.
Tip refinement is another overlap. Over-aggressive trimming of the lower cartilages can leave the nostril walls too weak to stay open on a strong breath. A more conservative approach, reshaping with sutures and support grafts, aims to refine the look while keeping the tip resilient.
Narrowing the nose has an obvious trade-off: a narrower structure leaves less room for air. Narrowing is not always ruled out, but your anatomy sets the limits. Thick skin, for example, will not shrink-wrap around a very refined framework, so pushing for an extremely small nose can bring both an unsatisfying look and a compromised airway.
Complex valve and tip work is often easier to perform accurately through an open approach, though not always; our article on open versus closed rhinoplasty covers the trade-offs.
A sensible plan starts from what your nose needs to work well, then asks which aesthetic changes are achievable within that. Patients sometimes find this frustrating at first, but a nose that looks pleasing and breathes poorly is rarely a happy outcome, and it is one of the more common reasons people later seek revision surgery.
Who septorhinoplasty is not for
Being clear about who should not have surgery is part of an honest consultation. Septorhinoplasty is unlikely to be right for you if:
- Your blockage is mainly due to allergies, rhinitis, polyps or sinus disease that has not yet been investigated or treated.
- You still rely on decongestant sprays, as rebound congestion needs to settle before structure can be assessed properly.
- You are under 18 or your face is still growing.
- You smoke or use nicotine and are not prepared to stop for a period before and after surgery, because nicotine impairs blood supply and healing.
- You have medical conditions or take medicines affecting bleeding or anaesthetic safety that have not been reviewed.
- You are hoping a new nose will resolve wider distress about your appearance. If you feel preoccupied by a flaw others do not notice, or previous procedures have not left you satisfied, we may suggest speaking to your GP or a psychological professional first. This is not a judgement; it is about making sure surgery is likely to help rather than harm.
- Your expectations are fixed on an exact result, such as an edited image or someone else's nose. Your own skin, bone and cartilage determine what is achievable.
Functional nasal surgery may also be available through the NHS for people whose breathing is significantly affected, subject to local criteria and GP referral. If your concern is purely functional, that route is worth exploring. Private surgery tends to suit people who want function and shape addressed together, or who prefer to plan their care privately for other reasons.
Recovery, risks and how breathing changes over time
One part of recovery that surprises many patients is that breathing usually feels worse before it feels better. In the first weeks, swelling of the lining, internal splints if used, and crusting can make the nose feel very blocked. This is expected and is not a sign that the operation has failed.
Septorhinoplasty is usually carried out under general anaesthetic, and depending on the plan you may go home the same day or stay overnight. An external splint is commonly worn for around a week. You will be advised to sleep with your head raised, avoid blowing your nose for a period, sneeze with your mouth open, use saline rinses as directed, and avoid strenuous exercise and contact sports for several weeks. Glasses may need to be kept off the bridge while the bones heal, and bruising around the eyes generally settles over a couple of weeks.
Airflow typically improves gradually over the following weeks and months as swelling reduces. The shape keeps evolving too: most visible swelling settles within the first few months, but the tip can stay subtly swollen and firm for a year or longer, especially with thicker skin. Judging the final appearance too early is one of the commonest sources of worry.
Every operation carries risks, and you should hear them plainly. They include bleeding, including nosebleeds after you go home; infection; reactions to anaesthetic; numbness of the tip or upper teeth, usually temporary; a hole in the septum, known as a septal perforation, which can cause crusting, whistling or bleeding; bands of scar tissue inside the nose; changes in sense of smell; persistent or recurrent blockage; irregularities, asymmetry or a shape you are unhappy with; a small scar under the tip if an open approach is used; and the possibility of further surgery. Your surgeon will explain how these apply to your nose and your operation.
Booking your consultation
If your nose feels blocked, looks different from how you would like, or both, the first step is a consultation rather than a decision. At our Kensington clinic consultations are doctor-led, and surgery is performed by Dr Hassan Soueid or one of our qualified surgeons.
It helps to come prepared. Note when your breathing problems started, which side is worse, any injuries, any sprays or medicines you use and whether they help, and any previous nasal surgery. Bring letters or scans from an ENT team if you have them. Think about what you would like to change, and equally about what you would like to keep, because many patients value features they do not want lost.
We will take a full medical history, examine your nose inside and out, explain whether the findings fit your symptoms and outline the options, which may be medical treatment, referral elsewhere or surgery. If surgery is appropriate we will go through what it involves, the recovery, the risks and the limits, and you will have time to reflect before deciding. You are always welcome to come back with more questions or to seek a second opinion.
We are introducing HonestFace, our own iPad app for digital consultation forms, consent signing and secure patient records, so in future you may be invited to complete some of your paperwork through it.
Kensington Cosmetic Clinic is registered with the Care Quality Commission, and we see patients from across London and beyond. When you are ready, you can book a consultation online or contact the clinic for more information.
Frequently asked
Questions we get asked
- Can I have surgery to improve my breathing without changing how my nose looks?
- Often the aim can be mainly functional. Straightening the septum is done from inside the nose and may leave the outside largely unchanged. However, if the valves need support or the nose is twisted externally, some visible change may be needed or unavoidable. We will explain what is likely in your case at consultation.
- Will septorhinoplasty stop my snoring?
- Not reliably. Snoring has many causes, most of them in the throat and soft palate rather than the nose. Septorhinoplasty is not a cure for obstructive sleep apnoea either. If sleep-disordered breathing is suspected, we may suggest assessment through your GP or an ear, nose and throat surgeon.
- Can dermal fillers fix a blocked nose?
- No. Filler can sometimes disguise a small bump or dip in the profile, but it does nothing to open the airway. Filler in the nose also carries particular vascular risks, so it needs careful discussion with a doctor rather than being treated as a simple alternative to surgery.
- How long does it take for breathing to improve after septorhinoplasty?
- Most people feel more blocked for the first few weeks because of swelling, crusting and any internal splints. Airflow then usually improves gradually over the following weeks and months. Swelling, particularly in the tip, can take a year or longer to settle fully, and how much breathing improves varies between individuals.
- Is functional nose surgery available on the NHS?
- Functional nasal surgery may be available through the NHS for people whose breathing is significantly affected, depending on local criteria and referral through your GP. If your concern is purely functional, it is worth exploring that route. Private surgery suits people who want breathing and shape addressed together or prefer to plan their care privately.